Disease-specific landmark atlas · Colon

Colon Cancer Landmark Atlas

Landmark studies on adjuvant oxaliplatin, treatment duration, ctDNA, neoadjuvant and adjuvant immunotherapy, and metastatic MSI-H/dMMR disease.

DFS, OS, pCR, cCR, and similar endpoints are not interchangeable. Gold stars are never assigned automatically. Numeric cards are verified summaries of primary publications. A patient summary is not a treatment recommendation.

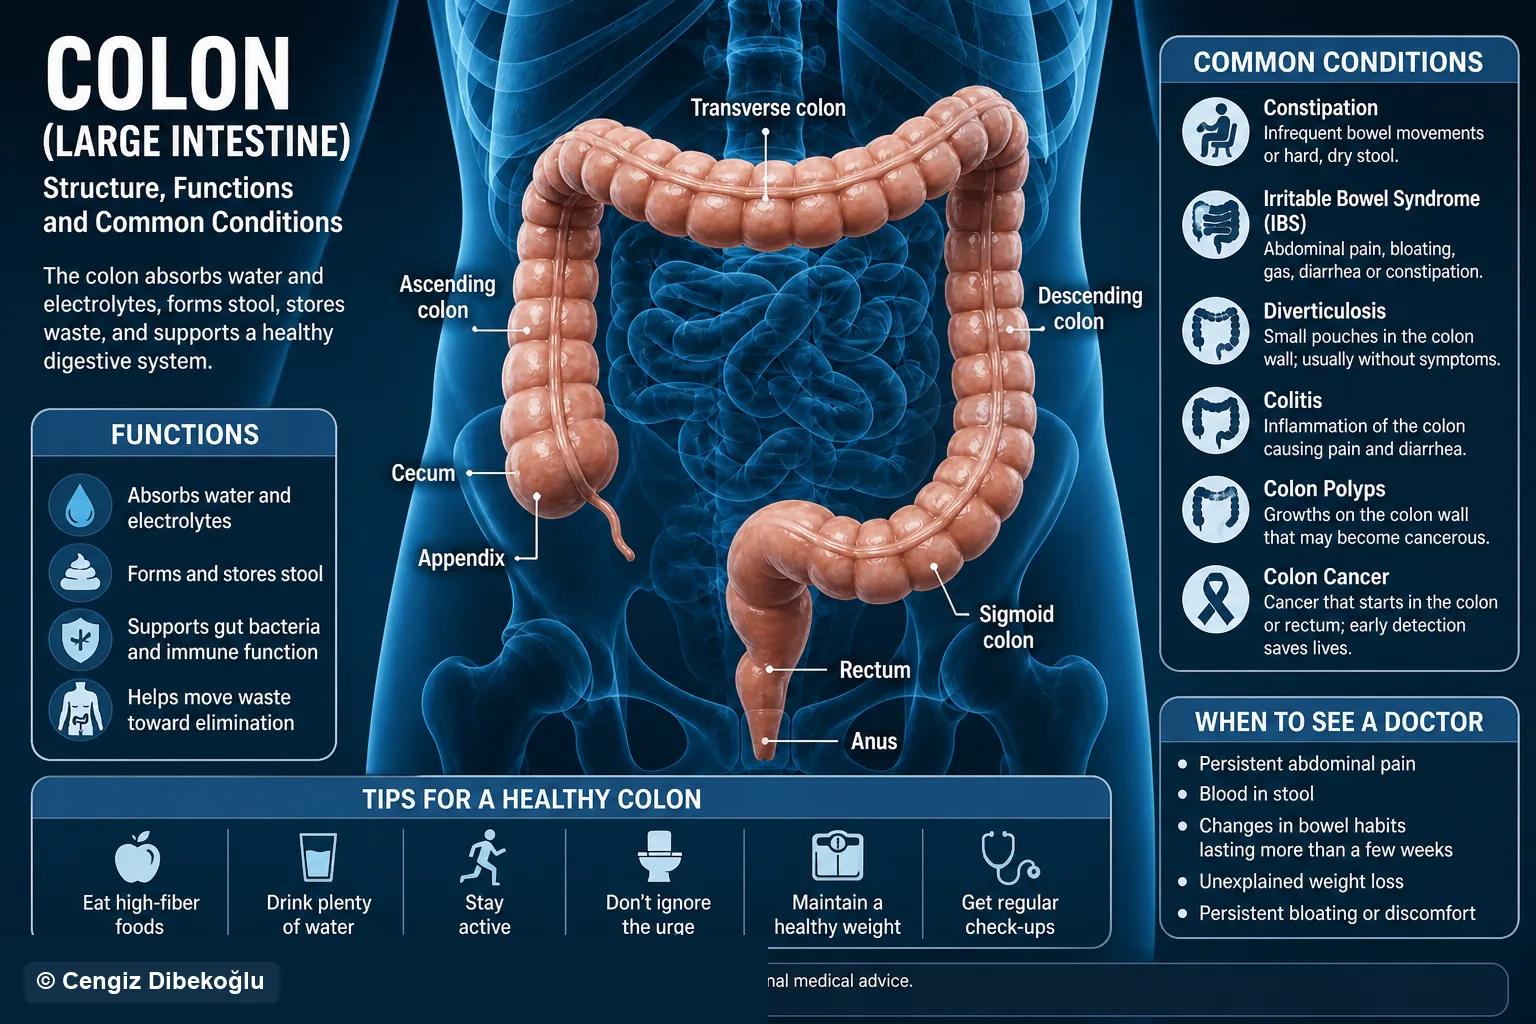
3D educational illustration: colon anatomy

How did treatment change?

In colon cancer, postoperative chemotherapy, duration choice, ctDNA, and immunotherapy evidence have separated treatment by stage and molecular subtype.

  1. Previous approach

    In stage III and selected high-risk disease, longer adjuvant chemotherapy was applied more uniformly; molecular subgrouping was limited.

  2. New clinical evidence

    Adding oxaliplatin, the IDEA duration debate, ctDNA-guided approaches, and immunotherapy studies in MSI-H/dMMR disease clarified who needs how much treatment and in what order.

  3. Current approach

    Adjuvant duration, neoadjuvant options, and metastatic sequencing are individualized by stage, risk, mismatch-repair status, and patient fitness.

This summary is for patient education; individual treatment decisions depend on stage, pathology, imaging, and physician assessment.

Landmark status

Sorting

Topic filters

Showing 13 studies.

Comparison table

Select 2 or 3 studies to compare. Different endpoints are never combined in one chart.

Open this discovery in the “Discoveries That Changed Cancer Treatment” hub

Colon cancer · postoperative chemotherapy

Gold Star — Paradigm-Changing2015 (10 -year update)Source verified

MOSAIC

What did the researchers want to learn?

In colon cancer removed by surgery, does adding oxaliplatin to classic fluorouracil treatment reduce the chance of the disease coming back?

Before

After surgery for colon cancer, the standard approach was mostly fluorouracil/leucovorin; adding oxaliplatin was not yet established everywhere.

Today

In suitable stage III patients, oxaliplatin-containing adjuvant regimens (the FOLFOX family) became a widely used standard option.

What did this study change?

Adjuvant (postoperative) FOLFOX and other oxaliplatin-containing regimens became the foundation of standard postoperative options in suitable colon cancer.

Benefit for patients

It concerns the postoperative treatment decision aimed at reducing recurrence risk in resected colon cancer, especially stage III.

What did the research find?

In stage III and selected high-risk patients, adding oxaliplatin lengthened the time without recurrence. The survival benefit is read separately by stage and by time point; not every early-stage patient needs the same regimen.

Who does this apply to?

Applies particularly to stage III and to selected high-risk stage II disease. In older, frail patients or those at high risk of neuropathy, duration and dose are individualized. It is not automatically applied to rectal cancer.

What did it not prove?

It did not prove overall survival superiority in stage II patients. It does not show that oxaliplatin is a neuropathy-free treatment.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Why this study has a gold star: It contributed to oxaliplatin-containing adjuvant regimens becoming the standard approach, particularly in suitable patients with stage III colon cancer. (2004–2009 / editorial 2026-10)

Colon cancer · postoperative chemotherapy

Foundational Evidence2011 (updated survival)Source verified

NSABP C-07

What did the researchers want to learn?

Does adding the drug oxaliplatin to standard chemotherapy given after surgery lengthen the time before the disease comes back?

Before

While adjuvant fluorouracil/leucovorin was frequently used, the DFS benefit of adding oxaliplatin still awaited confirmation in other large trials.

Today

The ability of oxaliplatin to improve disease-free survival in the adjuvant setting was strengthened by additional phase III evidence; regimen choice is read separately with contemporary FOLFOX/CAPOX.

What did this study change?

It supported the view that oxaliplatin can contribute to reducing the risk of recurrence in postoperative treatment. This benefit did not translate into a proven increase in overall survival.

Benefit for patients

It concerns colon cancer patients considered for postoperative oxaliplatin-containing chemotherapy.

What did the research find?

Five years later, the proportion of patients alive without recurrence was 69.4% in the oxaliplatin group and 64.2% in the control group. Five-year overall survival rates were 80.2% and 78.4%; in the updated analysis the difference in overall survival was not statistically significant.

Who does this apply to?

The FLOX regimen used in the study is not the same as the FOLFOX and CAPOX regimens commonly used today. Side effects and differences in administration are assessed separately for each person.

What did it not prove?

It did not show that the regimen is the same as contemporary FOLFOX/CAPOX, or that it proved definitive overall survival superiority. FLOX is not identical to todmo’s regimens.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Colon cancer · adjuvant duration

Foundational Evidence2020Source verified

IDEA Collaboration

What did the researchers want to learn?

In some patients, may 3 months of oxaliplatin-based chemotherapy after surgery be enough, or are 6 months needed?

Before

In stage III colon cancer, oxaliplatin-containing adjuvant therapy was often planned for six months; the safety of shortening duration was uncertain.

Today

Depending on T/N risk and CAPOX/FOLFOX choice, three months of treatment is discussed as a reasonable option for many patients; duration is individualized.

What did this study change?

A shorter adjuvant duration became a topic of discussion in selected patients in order to reduce the risk of neuropathy.

Benefit for patients

It concerns patients for whom the balance between postoperative chemotherapy duration and neuropathy risk in stage III colon cancer is being considered.

What did the research find?

In selected low-risk patients, 3 months of treatment may give results close to 6 months, whereas in high-risk disease 6 months may appear safer. The decision on duration varies by risk group.

Who does this apply to?

Risk group (T and N features) is critical. It is not correct to say 3 months for all patients.

What did it not prove?

It did not definitively show that three months is statistically non-inferior to six months in the overall population. CAPOX and FOLFOX results are not the same; it does not mean automatic short duration for high-risk T4/N2.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Colorectal cancer · duration of postoperative chemotherapy

Foundational Evidence2018Source verified

SCOT

What did the researchers want to learn?

In high-risk stage II and stage III colorectal (colon and rectal) cancer, is giving postoperative chemotherapy for three months as safe and effective as giving it for six months?

Before

In colorectal cancer, adjuvant oxaliplatin duration was close to six months in most practice; randomized evidence for a shorter course was limited.

Today

Three months of treatment provided evidence supporting oncologic outcomes while reducing neuropathy in selected patients; it is read together with IDEA.

What did this study change?

In decisions about treatment duration, not only the risk of recurrence but also lasting nerve side effects and quality of life can now be taken into account.

Benefit for patients

It concerns the adjuvant duration decision in high-risk stage II and stage III colon or rectal cancer.

What did the research find?

Three years later, the proportion of patients alive without recurrence was 76.7% with three months of treatment and 77.1% with six months; the study's prespecified non-inferiority criterion (that the shorter treatment was not worse) was met. In the subgroup with safety data, moderate or worse nerve damage (numbness, tingling) was reported in 58% with six months of treatment and 25% with three months.

Who does this apply to?

The study covers not only colon cancer but also rectal cancer. The drug regimen and risk group are important; this study is one of the datasets evaluated together with other studies addressing the same question and should not be read as a completely independent second piece of evidence.

What did it not prove?

It is not a colon-cancer-only trial. It alone does not prove that three months is mandatory or equivalent in every patient.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Stage II colon cancer · treatment decision guided by circulating tumor DNA in the blood

Emerging Evidence2022Source verified

DYNAMIC

What did the researchers want to learn?

In stage II colon cancer, can making the chemotherapy decision by looking at circulating tumor DNA in the blood reduce unnecessary chemotherapy while maintaining control of recurrence?

Before

In stage II colon cancer, the adjuvant chemotherapy decision was mostly based on pathologic risk features; ctDNA guidance was not routine.

Today

In selected centers, the ctDNA result entered the decision process with the potential to reduce unnecessary chemotherapy while preserving recurrence control.

What did this study change?

It showed that tests for residual disease in the blood may help personalize the need for chemotherapy in some patients. It cannot yet be said to have become the standard decision method for everyone in every center.

Benefit for patients

It concerns patients in whom whether postoperative chemotherapy is needed in stage II colon cancer is being discussed.

What did the research find?

Use of postoperative chemotherapy was 15% in the blood-test-guided group and 28% in the standard group. Two years later, the proportion of patients alive without recurrence was 93.5% and 92.4%, respectively; the study's prespecified non-inferiority criterion for the guided approach (that it was not worse) was met.

Who does this apply to?

Even when the test result is negative, it cannot be said with certainty that no microscopic cancer cells remain. The test method, the timing of the blood draw and long-term results are important; the findings apply only to stage II patients.

What did it not prove?

It shows that negative ctDNA does not definitively prove absence of microscopic disease. It does not mean a mandatory standard test for all stage II patients; it is not a long-term OS claim.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Colon cancer · mismatch repair deficiency (dMMR) · immunotherapy before surgery

Emerging Evidence2024Source verified

NICHE-2

What did the researchers want to learn?

In locally advanced colon cancer with mismatch repair deficiency (dMMR), does giving nivolumab and ipilimumab before surgery produce a strong response in the tumor?

Before

In early dMMR/MSI-H colon cancer, neoadjuvant immunotherapy was not standard; surgery was prioritized.

Today

In selected dMMR patients, high pathologic response rates with neoadjuvant immunotherapy were shown; it is discussed in multidisciplinary boards.

What did this study change?

It is important data showing that immunotherapy before surgery can produce a very high tumor response in dMMR colon cancer. Longer follow-up and comparative studies are needed for it to become established as a standard approach.

Benefit for patients

It concerns patients with dMMR/MSI-H features and planned surgery for colon cancer.

What did the research find?

In the tissue removed at surgery, regression of most of the tumor was reported in 98%, marked regression in 95%, and complete disappearance of the tumor (pathological complete response, pCR) in 68%. In the published analysis, no recurrence of the disease was observed at a median follow-up of 26 months.

Who does this apply to?

There is no comparison (control) group. Complete disappearance of the tumor at surgery is not a guarantee of lasting cure, and this study does not show that surgery can be safely omitted. It applies only to colon cancer with mismatch repair deficiency (dMMR).

What did it not prove?

It is not generalizable to pMMR disease. It alone does not prove that pathologic complete response means long-term overall survival superiority. It does not mean the same protocol in every center.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Metastatic colorectal cancer · microsatellite instability-high (MSI-H) / mismatch repair deficiency (dMMR) · first-line immunotherapy

Foundational Evidence2020 / 5y takip 2025Source verified

KEYNOTE-177

What did the researchers want to learn?

In colorectal cancer that is microsatellite instability-high or has mismatch repair deficiency (MSI-H/dMMR) and has not previously been treated with drugs for metastatic disease, does pembrolizumab give better results than standard chemotherapy?

Before

In metastatic MSI-H/dMMR colon cancer, first-line standard was often chemotherapy.

Today

In suitable MSI-H/dMMR metastatic patients, pembrolizumab was strengthened as a first-line option.

What did this study change?

It became one of the key studies that established first-line immunotherapy in MSI-H/dMMR metastatic colorectal cancer.

Benefit for patients

It concerns patients with microsatellite-unstable or dMMR metastatic colorectal cancer.

What did the research find?

Median progression-free survival (time before the disease progressed) was 16.5 months with pembrolizumab and 8.2 months with chemotherapy. At five years of follow-up, median overall survival was reported as 77.5 and 36.7 months; because a significant proportion of patients in the chemotherapy group later received immunotherapy, the survival results should be interpreted in this context.

Who does this apply to?

The findings cannot be applied to all patients with metastatic colorectal cancer; the biomarker microsatellite instability-high (MSI-H) or mismatch repair deficiency (dMMR) is required. The study covers tumors of both colon and rectal origin together.

What did it not prove?

It does not show the same benefit in MSS/pMMR disease. It does not prove that chemotherapy is replaced in all metastatic colon cancers.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Open this discovery in the “Discoveries That Changed Cancer Treatment” hub

Stage III colon cancer · mismatch repair deficiency (dMMR) · immunotherapy after surgery

Gold Star — Paradigm-Changing2026Source verified

ATOMIC

What did the researchers want to learn?

In operated stage III colon cancer with mismatch repair deficiency (dMMR), does adding atezolizumab to postoperative FOLFOX chemotherapy lengthen the time before the disease comes back (disease-free survival)?

Before

In stage III dMMR colon cancer, the adjuvant standard was mostly chemotherapy alone; adding immunotherapy had not been proven.

Today

In selected stage III dMMR patients, adding atezolizumab to adjuvant chemotherapy showed a DFS benefit; licensing/access differ by country.

What did this study change?

It showed a disease-free survival benefit from adding immunotherapy after surgery in stage III dMMR colon cancer. With FDA approval — 8 October 2026 (United States), an approved adjuvant option now exists for this indication. Licensing / reimbursement in Turkey is separate.

Benefit for patients

It concerns patients with surgically treated stage III dMMR colon cancer.

What did the research find?

At a median follow-up of about 41 months, the proportion of patients alive without recurrence at three years was 86.3% in the combination group and 76.2% in the control group (absolute difference about 10 percentage points; hazard ratio 0.50; p<0.001). This hazard ratio is a relative event rate; it does not mean a 50% reduction in absolute risk. Severe side effects (grade 3–4) occurred in 84.1% of the combination group and 71.9% of the control group. The difference in overall survival (total survival time) is not yet clear.

Who does this apply to?

Valid only for stage III colon cancer with mismatch repair deficiency (dMMR). Overall survival data are not yet mature; the increase in side effects should be monitored. FDA approval applies to the United States; it is not automatically considered standard in Turkey and other countries.

What did it not prove?

It did not show mature overall survival superiority. It does not automatically transfer to pMMR disease or to the NICHE-2 neoadjuvant pathwmo.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Why this study has a gold star: It showed a disease-free survival benefit of adding adjuvant immunotherapy in stage III dMMR colon cancer. FDA approval — 8 October 2026 (US): atezolizumab + fluoropyrimidine/oxaliplatin (regular approval, not accelerated). Physician approval 2026-10-29: gold star. (2026 NEJM + FDA 2026-10-08 · gold-star approval 2026-10-29)

Locally advanced colon cancer · chemotherapy before surgery

Foundational Evidence2023Source verified

FOxTROT

What did the researchers want to learn?

In locally advanced colon cancer that can be operated on, is it beneficial to give part of the chemotherapy before surgery?

Before

Preoperative chemotherapy was not routine in colon cancer; surgery first was planned for most patients.

Today

In selected locally advanced colon cancer, neoadjuvant chemotherapy became an option discussed for recurrence and surgical outcomes.

What did this study change?

It supported preoperative chemotherapy as an option in selected locally advanced colon cancers.

Benefit for patients

It concerns selected patients with resectable, locally advanced colon cancer.

What did the research find?

The rate of residual or recurrent disease within two years was 16.9% in the preoperative chemotherapy group and 21.5% in the control group (p=0.037). The rate of complete surgical removal of the tumor was about 94% vs 89%.

Who does this apply to?

Staging by computed tomography may make the disease appear more advanced than it is. In tumors with mismatch repair deficiency (dMMR), the benefit of this chemotherapy has appeared more limited; postponing surgery in patients at risk of bowel obstruction is assessed separately.

What did it not prove?

It does not show that neoadjuvant chemotherapy is mandatory in every colon cancer. It is not identical to rectal TNT protocols.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Metastatic colorectal cancer · MSI-H/dMMR · immunotherapy

Emerging Evidence2017+Study / result verification pending

CheckMate-142

What did the researchers want to learn?

In metastatic colorectal cancer with mismatch repair deficiency (dMMR) / microsatellite instability-high (MSI-H), is nivolumab effective alone or together with ipilimumab?

Before

Effective immunotherapy options in MSI-H/dMMR metastatic colorectal cancer were limited.

Today

Nivolumab (± ipilimumab) became an important systemic option in this molecular subgroup.

What did this study change?

It contributed to the development of immunotherapy strategies in dMMR/MSI-H metastatic colorectal cancer; it is not randomized evidence that on its own changed the standard.

Benefit for patients

It concerns patients with MSI-H or dMMR metastatic colorectal cancer.

What did the research find?

Clinically meaningful responses, and long-lasting responses in some patients, were shown with nivolumab-based treatments. The different patient groups (cohorts) were not compared directly with each other.

Who does this apply to?

Superiority cannot be inferred by comparing cohorts with each other. Tumors of colon and rectal origin may be included together. The level of evidence is not the same as that of KEYNOTE-177, a randomized phase III study.

What did it not prove?

It is not generalizable to MSS disease. It does not resolve the adjuvant early-stage question.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Locally advanced colon cancer · FOLFOX before surgery

Emerging Evidence2019 / 3y takip 2021Source verified

PRODIGE 22 / ECKINOXE

What did the researchers want to learn?

In high-risk locally advanced colon cancer, does giving FOLFOX chemotherapy before surgery increase tumor regression?

Before

Neoadjuvant strategies in locally advanced colon cancer had limited randomized evidence.

Today

The place of a neoadjuvant approach in selected patients was opened to discussion; it is read together with FOxTROT and other trials.

What did this study change?

Before the FOxTROT study, it provided early evidence that preoperative chemotherapy is feasible; on its own it did not change the standard.

Benefit for patients

It concerns selected patients with locally advanced colon cancer.

What did the research find?

Tumor regression was seen in the group receiving FOLFOX before surgery. The study was not designed to prove a survival advantage.

Who does this apply to?

Because of the small number of patients, the early-phase (phase II) design and limited statistical power for survival, no conclusions can be drawn about survival time.

What did it not prove?

It does not prove that neoadjuvant therapy is standard in all colon cancers.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Early-stage colorectal cancer · postoperative chemotherapy decision

Foundational Evidence2007Source verified

QUASAR

What did the researchers want to learn?

In operated early-stage colorectal cancer in which the need for additional chemotherapy is uncertain, does fluorouracil-based chemotherapy provide a benefit?

Before

The benefit of adjuvant fluorouracil in stage II colon cancer was uncertain; chemotherapy was not given to everyone.

Today

It was shown that adjuvant fluorouracil mmo have a small survival benefit in selected stage II patients; decisions continue according to risk features.

What did this study change?

It supported the view that in stage II patients the chemotherapy decision should be made individually, weighing the expected small benefit against side effects.

Benefit for patients

It concerns patients in whom the chemotherapy decision after resected stage II colon cancer is being discussed.

What did the research find?

Postoperative chemotherapy showed a modest reduction in the risk of recurrence and death. The absolute benefit is limited and is weighed together with side effects.

Who does this apply to?

A large part of the study was conducted before today's molecular classification and modern chemotherapy regimens; it covers colon and rectal cancer together. It cannot be applied one-to-one to a patient today.

What did it not prove?

It does not mean mandatory chemotherapy for all stage II patients. It does not show that modern oxaliplatin-containing regimens are mandatory.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Stage III colon cancer · adding celecoxib to postoperative treatment

Emerging Evidence2021Source verified

CALGB/SWOG 80702

What did the researchers want to learn?

In stage III colon cancer, does adding the drug celecoxib to standard postoperative chemotherapy lengthen the time before the disease comes back?

Before

The benefit of agents such as celecoxib added after adjuvant FOLFOX was unclear.

Today

DFS superiority of adding celecoxib on top of adjuvant FOLFOX was not supported in this trial; the standard FOLFOX duration discussion is separate.

What did this study change?

It did not support routinely adding celecoxib to postoperative chemotherapy; negative studies are also valuable in showing what should not be done in practice.

Benefit for patients

It concerns the discussion of additional drugs in colon cancer patients receiving postoperative FOLFOX.

What did the research find?

In the overall patient group, adding celecoxib did not show a significant advantage in the time before the disease came back; that is, the main goal of the study was not met.

Who does this apply to?

Additional analyses in specific molecular subgroups cannot be generalized as a treatment recommendation for all patients.

What did it not prove?

It does not show that FOLFOX itself is useless. It does not cover different NSAIDs or duration protocols.

This summary is not a treatment recommendation. Decisions depend on the type of disease, stage, general health, and your physician's assessment.

Atlas comparison guide

Adjuvant therapy — MOSAIC / NSABP C-07 / QUASAR

MOSAIC and NSABP C-07 support the adjuvant benefit of oxaliplatin (especially in stage III); the regimens (FOLFOX4 vs FLOX) are not equivalent. QUASAR shows a modest absolute benefit of fluorouracil-based therapy in stage II; it predates modern molecular classification and is mixed colorectal. The three are not the same patient population.

Treatment duration — IDEA / SCOT

Shorter treatment may be considered in the appropriate risk and CAPOX context. SCOT is one of the trials contributing data to the IDEA analysis; it should not be read as a fully independent second evidence set. SCOT includes a mixed colorectal population.

Neoadjuvant chemotherapy — FOxTROT / PRODIGE 22

Both study preoperative chemotherapy in locally advanced colon cancer. FOxTROT is the larger randomized mature result (2y disease control). PRODIGE 22 is phase II; the primary endpoint is pathologic regression and it was not designed for OS superiority. Evidence levels differ.

Molecular guidance — DYNAMIC / NICHE-2 / ATOMIC

DYNAMIC: ctDNA-guided chemotherapy selection in stage II; NICHE-2: neoadjuvant immunotherapy in locally advanced dMMR (pathologic response); ATOMIC: adjuvant chemotherapy + atezolizumab in stage III dMMR (DFS). Stage and treatment timing differ — pCR, DFS, and ctDNA decisions are not interchangeable.

Metastatic immunotherapy — KEYNOTE-177 / CheckMate-142

KEYNOTE-177 is randomized phase III (pembrolizumab vs chemotherapy). CheckMate-142 is a nonrandomized multi-cohort phase II. Evidence levels must be kept separate; cohorts cannot be used for a direct superiority comparison with KEYNOTE.

NICHE-2 and ATOMIC — shared dMMR, what differs?

NICHE-2 is preoperative immunotherapy and pathologic response; ATOMIC is postoperative DFS. pCR and DFS percentages cannot be compared directly.

Medical editor's note

Each study was designed for a specific patient group, treatment arm, and primary endpoint. Results should not be automatically generalized to other diseases or to all patients. This atlas is educational and is not a treatment recommendation.

Evidence

Scientific sources

Show sources · 3

Colon cancer landmark atlas: MOSAIC, NSABP C-07, IDEA, SCOT, DYNAMIC, NICHE-2, KEYNOTE-177, ATOMIC. DFS/OS/PFS are not interchangeable; SCOT and KEYNOTE-177 include mixed colorectal populations. Numeric cards live only on this page.

  1. Metastatic colorectal cancer: ESMO Clinical Practice Guideline for diagnosis, treatment and follow-upEuropean Society for Medical Oncology (ESMO) · 2023 · DOI: 10.1016/j.annonc.2022.10.003Open source
  2. NCCN Clinical Practice Guidelines in Oncology: Colon CancerNational Comprehensive Cancer Network (NCCN) · Current versionOpen source
  3. ASCRS clinical practice guidelines libraryAmerican Society of Colon & Rectal Surgeons (ASCRS) · Guideline libraryOpen source

Source list last checked: 31 October 2026. (Page content review date may appear separately above.)